Toggle light / dark theme

Stereotactic Radiotherapy vs HippocampalAvoidance Whole Brain Radiation

As patients live longer with advanced cancer, brain metastases are now becoming a frequent and even chronic condition managed with a variety of systemic agents and local treatments.1 Radiotherapy plays a key role in treatment of intracranial lesions. Whole brain radiation therapy (WBRT) has the benefit of treating both imaging-apparent and microscopic disease. This approach can offer general intracranial disease control, but can damage healthy brain tissue, resulting in neurocognitive impairment associated with irradiation of the hippocampus.2 The innovation of hippocampal-avoidance WBRT (HA-WBRT) maintains global intracranial disease control while reducing neurocognitive decline relative to traditional WBRT, even in the setting of the neuroprotectant memantine (0.74; 95% CI, 0.58−0.95; P = .02), making HA-WBRT a standard-of-care approach to appropriate patients.3-5 Nevertheless, HA-WBRT requires several weeks of daily treatments and often time off systemic therapy. Conversely, stereotactic radiation (SRT) is given over 1 to 3 treatments to the visible lesions, allowing for higher radiation dose, better focal disease control, and sparing of healthy brain tissue, which further reduces neurocognitive toxic effects. SRT is appropriate for patients with a finite number of visible lesions but may allow microscopic disease elsewhere in the brain to progress, necessitating subsequent treatments or even salvage WBRT. In addition, the higher dose of SRT can cause radiation necrosis and inflammation, requiring steroids or other medical and surgical interventions.4 The optimal balance of intracranial disease control with patient-reported outcomes (PROs) is of increasing importance as patients live longer with the subacute and chronic toxic effects of radiotherapy.

To find that balance, multiple randomized clinical trials have confirmed that SRT offers improved efficacy and PROs compared with WBRT in patients with 1 to 4 brain metastases.2, 6-9 However, with advances in systemic therapy and surveillance, patients now frequently present with multiple brain metastases, high performance status, and expected survival of months to years. Without any high-level evidence comparing the efficacy and toxic effects of HA-WBRT with SRT in patients with 5 or more brain metastases, radiation oncologists have been left to make recommendations between each modality on a case-by-case basis. Shared decision-making attempts to account for lesion number, velocity, distribution, size, histologic findings, symptomatology, available systemic therapeutics with central nervous system penetrance, treatment goals, and tolerance for cognitive decline.

Daytime cortisol patterns track cognitive decline but not Alzheimer’s disease risk

In 3,895 older adults, moderate daytime cortisol variability was associated with better cognition and slower decline, while the highest daily cortisol exposure was linked to poorer cognition and faster decline. Cortisol patterns differed between Black and White participants, but their relationships with cognition were similar, and none predicted incident Alzheimer’s disease.

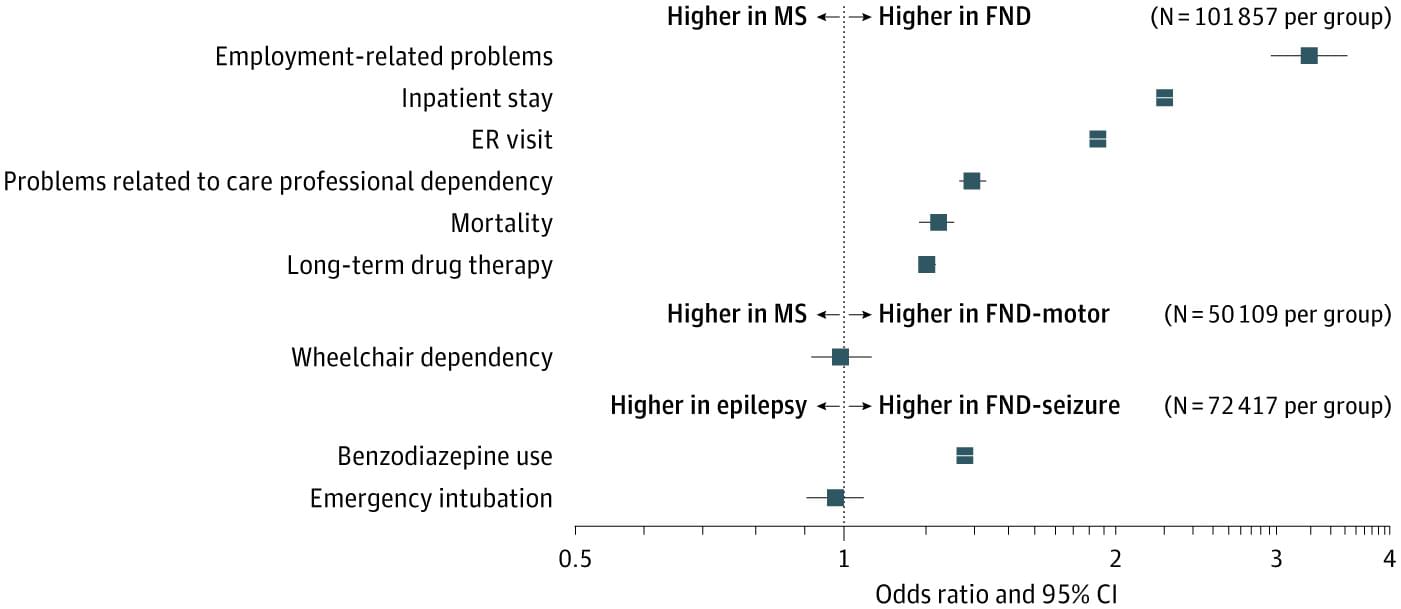
Comorbidities and Outcomes in People with Functional Neurological Disorder

In this cohort study, we retrospectively analyzed a large FND cohort using TriNetX, a federated health research platform aggregating electronic health records from approximately 160 million individuals across 143 health care organizations in 17 countries. Diagnoses follow standardized clinical coding. Reporting adhered to the STROBE guideline. This study was exempt from IRB review and informed consent given the use of deidentified data, according to the Common Rule (45 CFR §46) and UK regulations from the Health Research Authority.

Demographics and lifetime comorbidities were extracted for patients with an initial F44.4-F44.7 diagnosis between 1995 and 2024. Clinical outcomes were compared between matched cohorts with an initial diagnosis between 2015 and 2024 to reflect contemporary care for all FND vs multiple sclerosis (MS; G35), FND-motor vs MS, and FND-seizure vs epilepsy (G40), controlling for age, sex, race, and ethnicity via propensity score matching, testing 2-sided z tests on absolute risk differences at a significance level of P .05 after Bonferroni correction for multiple comparisons, and calculating odds ratios with 95% CIs. Data extraction and analyses were performed in April 2025 on the web-based interface TriNetX LIVE. Full methods are described in eMethods 1 to 3 in Supplement 1.

Role of the Upper Motor Neuron in the Generation of Fasciculations in Early Disease Stages of Amyotrophic Lateral Sclerosis

Background and ObjectivesThe origin of fasciculation potentials (FPs) in the early stages of amyotrophic lateral sclerosis (ALS) remains a subject of debate. We investigated the role of the motor cortex in FP generation by comparing resting FP frequency…

Targeting EpsteinBarr virus (EBV) for treatment of multiple sclerosis

Epstein-Barr Virus (EBV) is now recognized as an essential causal agent in the development of Multiple Sclerosis (MS). MS is a chronic autoimmune disease resulting in demyelination and neurodegeneration in the central nervous system (CNS). EBV is a ubiquitous human γ-herpesvirus that establishes long-term latent infection in a small subpopulation of memory B-lymphocytes. While EBV and B-lymphocytes are known to be drivers of MS autoimmune disease, it remains enigmatic how a small population of EBV-infected cells trigger and drive MS pathogenesis in some individuals. In this review, we discuss the known biology of EBV and its role in MS and other disease, including cancers, where EBV is an essential driving factor in disease progression. We review some of the conditions and cofactors that increase the risk of EBV infection leading to MS and the potential of pharmacological, biologic and vaccine approaches to more selectively target EBV to treat MS.

Keywords: EBNA1; Episome; Latency; Multiple Sclerosis; Therapeutics.

Copyright © 2026. Published by Elsevier B.V.

The Wetware Spectrum: How the Brain Runs on Analog Waves, Digital Spikes, and Probabilistic Dreams

There is a habit of mind so embedded in Western intellectual history that we barely notice it anymore: when we want to understand the brain, we reach for the most sophisticated machine available and say, in effect, the brain is something like that. This is not merely a rhetorical convenience. It is a cognitive strategy — perhaps the only one available to us — for peering into an organ that cannot be fully observed from the inside, from the outside, or from anywhere in between. The machine metaphor is the mind’s mirror, and like all mirrors, it tells us something true and something distorted at the same time.

Ten‐year cognitive outcomes following epilepsy surgery: Temporal lobectomy versus selective amygdalohippocampectomy

Objective This study aimed to assess long-term memory outcomes in patients with temporal lobe epilepsy (TLE) who underwent anterior temporal lobectomy (ATL) or selective amygdalohippocampectomy (SAH), compared to nonoperated TLE over a 10-year follow-up period.

Obstructive sleep apnea in people with epilepsy: Modifying risk

Obstructive sleep apnea (OSA) is a common but underdiagnosed and undertreated sleep disorder among people with epilepsy (PWE). In PWE, this sleep disorder is often managed as a comorbid condition rather than a contributor to epilepsy outcomes. For many years, OSA has been associated with higher seizure burden and interictal epileptiform discharges. Emerging evidence links OSA to late onset epilepsy (LOE) and increased risk markers for sudden unexpected death in epilepsy (SUDEP). This evidence also suggests that treating OSA with continuous positive airway pressure may improve seizure control. This critical review of the literature posits that OSA should be viewed as a modifiable risk factor for PWE. We apply the Bradford Hill criteria for causation as a framework to appraise the evidence connecting OSA with seizure severity, incident LOE, and SUDEP risk.

Personalized gene therapy helps teen with rare form of severe epilepsy walk independently

SCN2A-related developmental epileptic encephalopathy (DEE) is a rare, severe form of childhood epilepsy and one of the most common causes of monogenic autism. The condition is caused by single mutations in the sodium voltage-gated channel alpha subunit (SCN2A) gene, which controls the flow of sodium ions into neurons. These mutations promote abnormal brain excitability, resulting in uncontrolled seizures along with developmental delays, autism, movement problems and gastrointestinal issues. Most of these mutations are de novo (not inherited from a parent) and arise spontaneously.

Traditional antiseizure medications are often ineffective and do not address the underlying genetic cause of SCN2A-related DEE.

Now, an international team of researchers led by the University of California San Diego and Rady Children’s Institute for Genomic Medicine has treated two children with the condition using gene therapy tailored to each child’s specific SCN2A mutation.

/* */