Toggle light / dark theme

Get the latest international news and world events from around the world.

Log in for authorized contributors

Recovering from a therapeutic stall in higher-risk myelodysplastic syndromes: re-examining biology, backbones and study designs

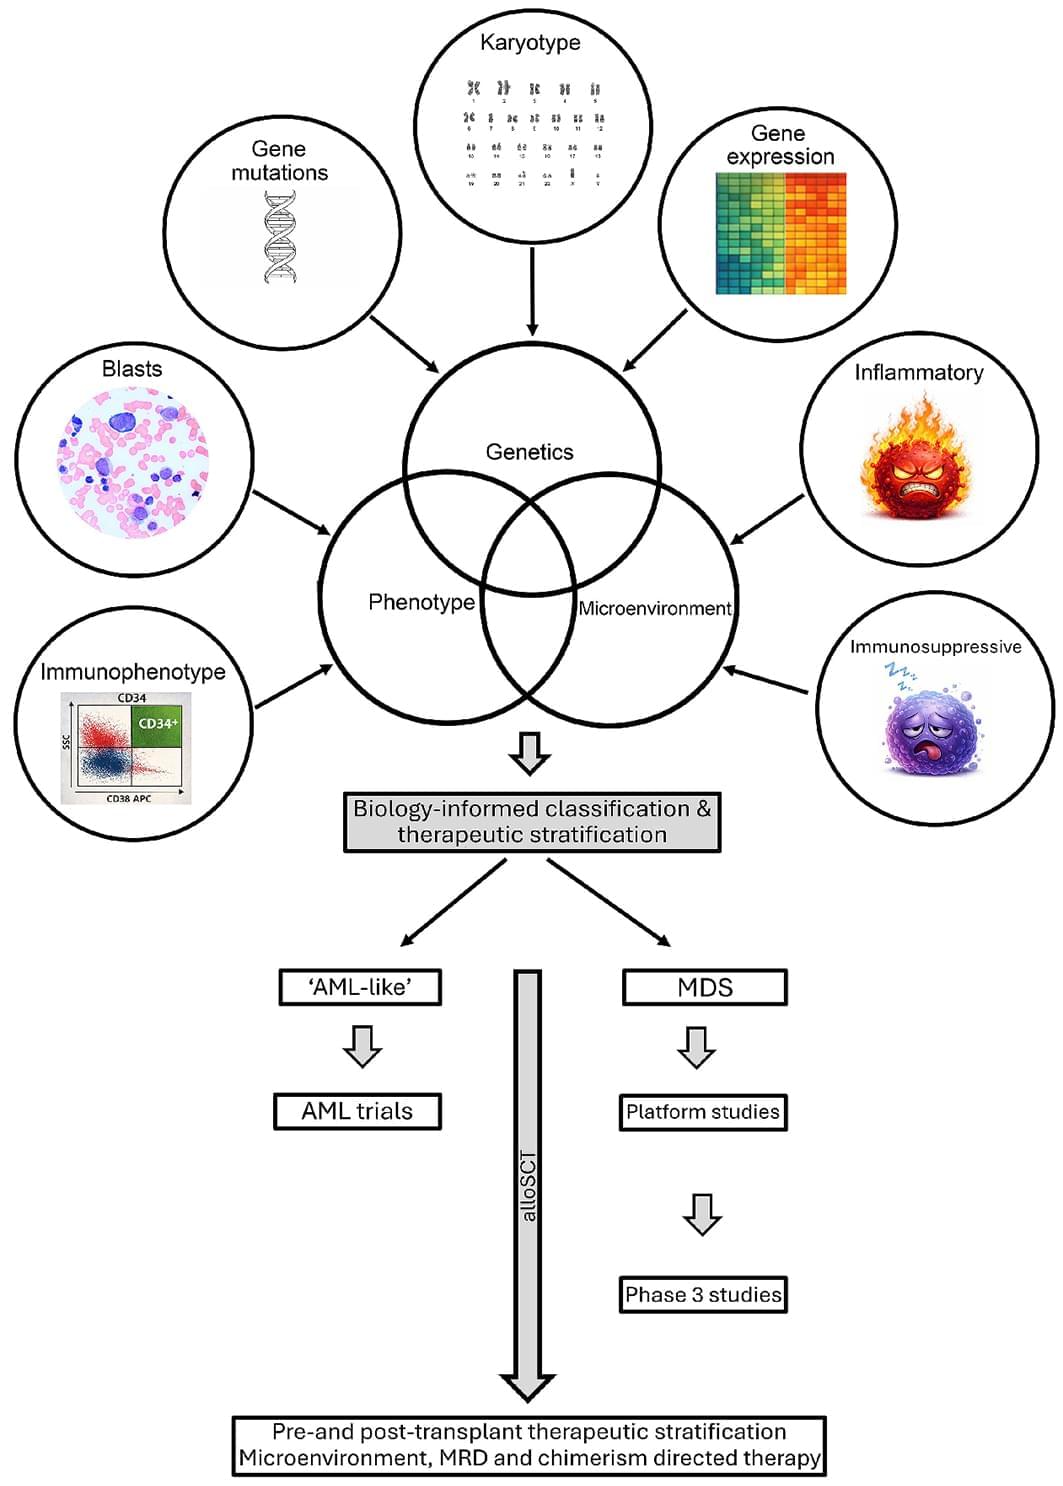
Therapeutic progress in higher-risk myelodysplastic syndromes (HR-MDS) has stalled. Despite repeated attempts to improve outcomes through incremental refinements to classification systems and hypomethylating agent (HMA)-based backbones, no phase III study since AZA-001 has replicated even the modest survival benefit observed with azacitidine. We propose that this stagnation results from a fundamental mismatch between the biological realities of HR-MDS and the assumptions underpinning contemporary drug development. HR-MDS encompasses biologically diverse ecosystems characterized by distinct clonal architectures, evolutionary trajectories and marrow microenvironmental dysfunction, despite overlapping phenotypic and genotypic features. Treating this heterogeneity as a single entity anchored to a HMA backbone, risks obscuring therapeutic signals and misinterpreting responses. Here, we examine the potential biological, microenvironmental, and methodological drivers of therapeutic insufficiency in HR-MDS, to advocate for biologically coherent adaptive platform trials using biomarker-enriched selection of patients, and propose shifting away from default HMA backbones. Only by redesigning strategy around biology, rather than prioritizing ease of recruitment, or historical precedent, can we restore momentum and lift in HR-MDS drug development.

In higher-risk myelodysplastic syndromes (HR-MDS), promising agents from early-phase clinical studies have repeatedly failed to improve survival in phase III trials of previously untreated patients.1–4 Much like an aircraft entering a slow-speed stall, continued progression along the same trajectory, through minor adjustments to existing frameworks or trial designs, risks deepening descent. Recovery will require abandoning ingrained reflexes and embracing counterintuitive inputs, including a biological and phenotypic re-examination of disease boundaries, rethinking trial design, and aligning trial endpoints with outcomes meaningful to patients. Recent reviews have elegantly summarized lessons from contemporary trials in treatment-naïve HR-MDS, highlighting opportunities to refine study design and endpoints.1–4

Here, we extend this discussion by focusing on relatively under-explored biological constraints related to disease dynamics, microenvironmental dysfunction, and treatment backbones, beginning with the challenge of defining what constitutes ‘HR-MDS’. In practice, this umbrella term is pragmatic but imprecise, encompassing patients defined by increased blast burden, adverse genetic features, or combinations of these factors, in whom variable degrees of marrow failure represent a shared phenotypic feature.5,6 Reliance on prognostic frameworks, such as the Revised International Prognostic Scoring System (IPSS-R)7 or Molecular International Prognostic Scoring System for Myelodysplastic Syndromes (IPSS-M),8 designed to estimate risk rather than to inform therapeutic strategy, has shaped clinical trial enrollment in HR-MDS and contributed to the uniform therapy of biologically heterogeneous diseases.

Cytotoxic CD8+ T cells in cancer and cancer immunotherapy

The natural immune response relies on the interaction of adaptive and innate immunity systems and the synergy between them. The essential aspects of this response in terms of anticancer immunity are the surveillance, detection and destruction of neoplastic cells. However, despite meticulous immune surveillance, cancer might eventually gain a foothold, and most immune cells will polarise into pro-tumorigenic or anti-tumorigenic cells, depending on a multitude of activating and inhibitory signals derived from cancer cells and their microenvironment. The outcome of this balance is a strong predictor of clinical outcome, with the infiltration of immune cells into, or their exclusion from, a tumour also being critical to the efficacy of immunotherapy.

Cytotoxic CD8+ T cells of the adaptive immune system are the most powerful effectors in the anticancer immune response and constitute the backbone of cancer immunotherapy. Immune-checkpoint inhibitors aim to block suppressive immune receptors and revitalise dysfunctional T cells, including CD8+ T cells, and adoptive cell transfer uses CD8+ T cells with genetically modified receptors (chimaeric antigen receptors [CARs]). Both approaches have had enormous impacts on the outcomes of various cancers; indeed, the field of immuno-oncology has revolutionised the treatment of cancer in terms of efficacy and personalised treatment options, as monotherapy or combinatorial regimens, and will continue to do so in the years to come. Nevertheless, any positive responses might not last, and the side effects could force treatment discontinuation, indicating the need to continuously improve treatment strategies. New pathways and immune checkpoints are being investigated, and new generations of CAR T-cell products are currently being evaluated in clinical trials. This review summarises advances in research into cytotoxic CD8+ T cells, the most prominent effector cell type in cancer and cancer immunotherapy.

Leg issue could be early Alzheimer’s symptom way before memory loss

The study was led by James Hickman and Xiufang “Nadine” Guo at the UCF, with researchers from healthcare tech company Hesperos. Guo said: “Motor deficits may be an earlier indication [of Alzheimer’s]. If we can detect those changes and intervene earlier, that could help delay the onset of central nervous system symptoms.”

Alzheimer’s is most commonly associated with memory loss, confusion and other difficulties with thinking. But doctors have also found that some people experience physical changes — including issues with balance and coordination — years before cognitive symptoms show up.

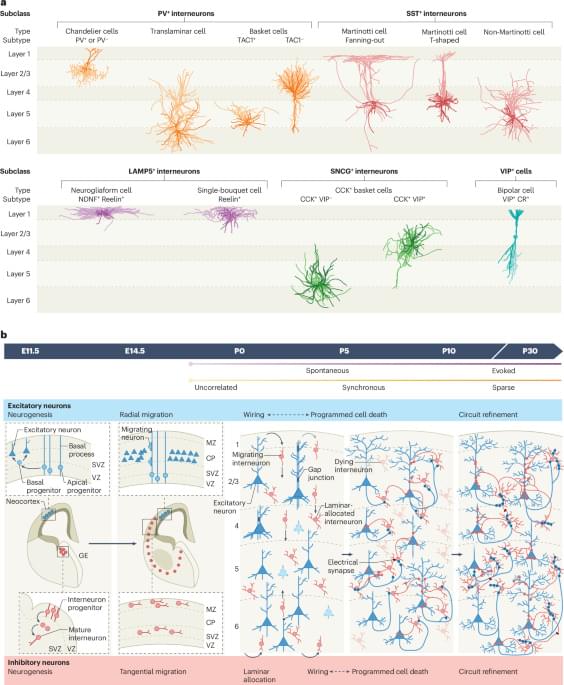
Interneurons and network activity in the cerebral cortex: a developmental dialogue

Neuronal activity is traditionally viewed as instructing cortical interneuron development. In this Review, Moissidis and Marín discuss how interneurons also actively shape early postnatal network activity, establishing a reciprocal dialogue that drives the maturation of both interneurons and cortical circuits.

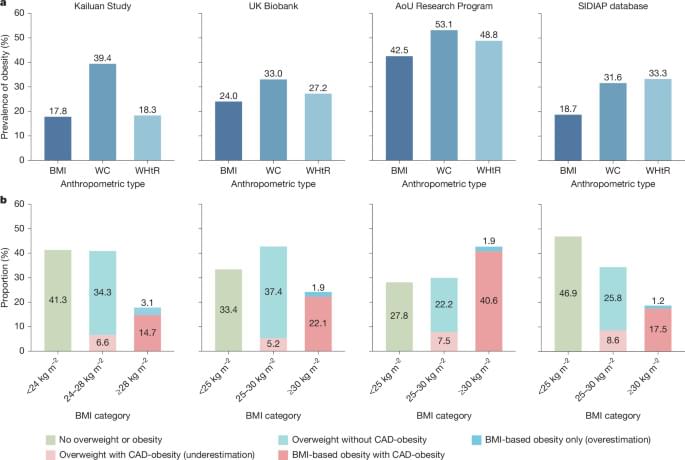
Validation of clinical and preclinical obesity across global cohorts

A large-scale data analysis assesses the Lancet Commission’s proposed diagnostic framework for obesity, finding that this framework, in which BMI is combined with other criteria, such as waist circumference and organ function, is more useful than classifications based on BMI alone.

Technology inspired by 3D printing could transform how medicines are tailored to patients

Technology inspired by 3D printing is already being introduced in hospitals and specialized pharmacies to produce personalized medicines tailored to individual patients. In her doctoral thesis at Åbo Akademi University, Mahsa Bahman investigated how the approach can improve dosing accuracy and make customised treatments more widely available.

Many medicines today are produced in standard doses, even though patients often have very different treatment needs. In her doctoral thesis in drug development at Åbo Akademi University, Mahsa Bahman investigated a technology that could make it easier to produce medicines tailored to individual patients, helping improve dose accuracy and access to treatment.

Personalised medicines are particularly important for children, older patients and others who require doses that are not commercially available. Today, healthcare professionals and caregivers may need to split tablets or adapt existing medicines, which can make accurate dosing difficult.