A company has created dogs that do not have the main protein that provokes allergies, and hopes to get approval to start selling them

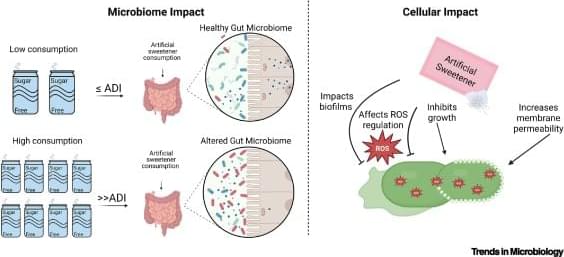
Artificial sweeteners are non-nutritive compounds that have a profound sweetening effect with a negligible to zero calorific contribution. Global initiatives to reduce sugar consumption to tackle health conditions such as obesity have led to a significant increase in their consumption in recent decades. Artificial sweeteners have undergone extensive testing to determine whether their consumption could impact human health; however, their impact on the microbiome and microbial physiology has been comparatively overlooked. Recent work has demonstrated that artificial sweeteners (e.g., Ace-K, saccharin, and aspartame) can influence the oral and gut microbiome and that they can significantly affect bacterial behavior and growth. In this review, we will contextualize these findings and explore their relevance to human artificial sweetener consumption.

GLP-1 drugs such as Ozempic have transformed healthcare in recent years, dramatically altering how we treat conditions like type 2 diabetes and obesity.
But while the medications are primarily used to help lower blood sugar and reduce appetite, scientists keep finding GLP-1 effects appear to extend much further, affecting our health in ways we never expected.
Now, a new study has uncovered another unintended effect, and it shows we’re still only scratching the surface of fully understanding how GLP-1 receptor agonists impact the body.

Soft sensors convert movement, temperature and moisture into electrical signals. Repeated bending and friction can cause their metal conductors to peel from the underlying polymer, while physical damage, such as cuts, can disable the device. Commonly used petroleum-derived substrates are also environmentally unfriendly because they are difficult to recycle.
Researchers at the College of Design and Engineering at the National University of Singapore (NUS CDE) have developed a soft, stretchable substrate that repairs itself, firmly grips metal conductors and can be remolded or broken down after use. It could make wearable patches and electronic skin used in applications such as health monitoring and virtual reality more durable while enabling the recovery of valuable components, thus reducing electronic waste.
The new material, called an intrinsically dynamic biosubstrate (IDBS), was developed by researchers led by assistant professor Zhai Wei from the Department of Mechanical Engineering at NUS CDE. Their findings were published in Nature Sustainability on June 19, 2026.
However, Carpenter was not entirely convinced that hyposalivation drives periodontitis. “I don’t think there’s much evidence for that in…literature about human studies,” he said. Instead, he said that inflammation—which is present in Dp16 salivary glands—could cause hyposalivation. “There’s lots of literature that shows that inflammatory cells can affect salivary secretion,” he noted.
According to Yule, next steps could include looking at whether dysregulated calcium signaling—which is linked with several other diseases—also underlies other Down syndrome-related complications like Alzheimer’s disease. While drugs targeting calcium signaling could potentially help, there is a complexity to it, he noted. “Knowing what the target is [is] good, but the fact that the target is almost universal in cells, then that makes you think about whether it’s something that could be targeted,” explained Yule.
Lacruz agreed that disrupted calcium signaling occurs in other tissues as well. “Understanding why calcium is dysregulated is an important part of what we need to do [next],” he said. More work needs to be done to translate the findings to the clinic, “but we see that as a way forward to potentially impacting the lives of individuals with Down syndrome,” said Lacruz.

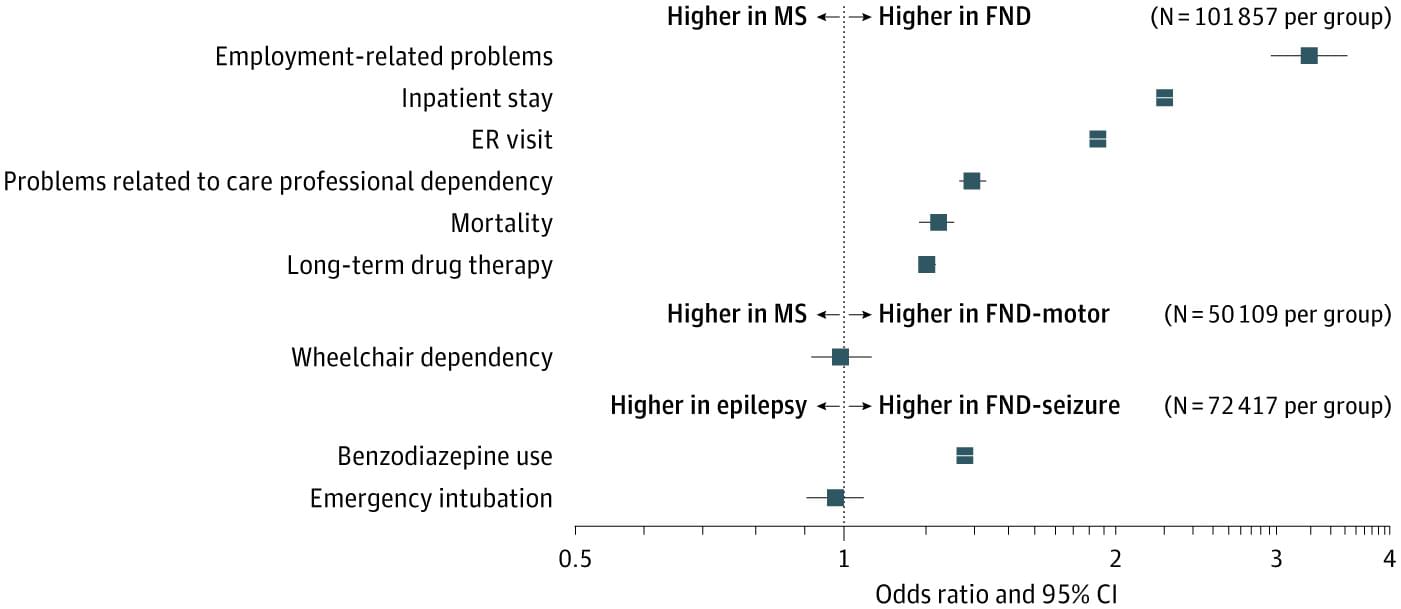
In this cohort study, we retrospectively analyzed a large FND cohort using TriNetX, a federated health research platform aggregating electronic health records from approximately 160 million individuals across 143 health care organizations in 17 countries. Diagnoses follow standardized clinical coding. Reporting adhered to the STROBE guideline. This study was exempt from IRB review and informed consent given the use of deidentified data, according to the Common Rule (45 CFR §46) and UK regulations from the Health Research Authority.
Demographics and lifetime comorbidities were extracted for patients with an initial F44.4-F44.7 diagnosis between 1995 and 2024. Clinical outcomes were compared between matched cohorts with an initial diagnosis between 2015 and 2024 to reflect contemporary care for all FND vs multiple sclerosis (MS; G35), FND-motor vs MS, and FND-seizure vs epilepsy (G40), controlling for age, sex, race, and ethnicity via propensity score matching, testing 2-sided z tests on absolute risk differences at a significance level of P .05 after Bonferroni correction for multiple comparisons, and calculating odds ratios with 95% CIs. Data extraction and analyses were performed in April 2025 on the web-based interface TriNetX LIVE. Full methods are described in eMethods 1 to 3 in Supplement 1.

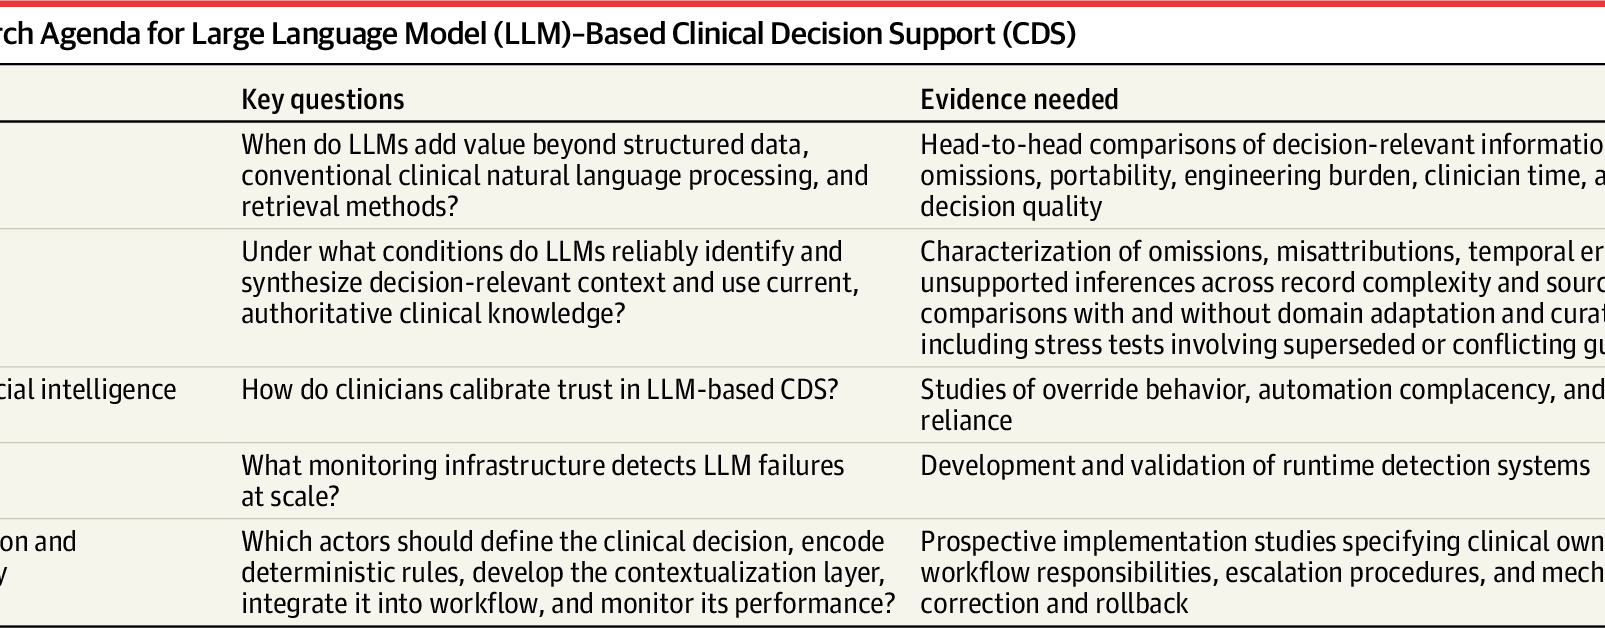
Consider a primary care physician seeing a patient aged 58 years for routine follow-up. The electronic health record (EHR) alerts that the patient is eligible for statin therapy. The physician overrides it, as clinicians do for the vast majority of alerts. The system verifies what is computationally easy (eg, age, lipid values, and risk score) but ignores what the clinician needs: has this patient been offered statins before? Did they decline, and if so, why (cost concerns, fear of adverse effects, preference for lifestyle modification)? Have they tried statins previously and experienced muscle pain? If they were prescribed a statin, did they ever pick it up from the pharmacy? What did they write in that patient portal message 2 months ago when they mentioned reading online that statins cause memory problems? The answers are scattered across notes, dispensing records, and portal messages. The alert identifies eligibility but not the patient’s decision state or the barriers to action.
Consistent with established definitions, clinical decision support (CDS) includes tools that provide knowledge and patient-specific information to support health decisions and is not limited to guideline adherence.1,2 This Perspective focuses on clinician-facing CDS organized around a defined decision; generic note drafting, inbox management, and open-ended chart summarization are excluded unless they directly support that decision. A prior reason for declining statin therapy is relevant because it changes the next action, not eligibility. Deterministic methods remain preferable when criteria and outputs are explicit; large language models (LLMs) may extend them through flexible synthesis and adaptive presentation.
Early medical LLM applications have focused on drafting replies and summarizing charts.3,4 The larger opportunity is to revisit a long-standing trade-off between clinical fidelity and computational tractability. Health information technology has historically represented complex narratives and knowledge through structured fields and rules because they were computable.5 LLMs do not provide the first access to narrative text; their incremental value is the flexibility to extract, synthesize, and communicate across heterogeneous sources.